Cardio Therapeutic Updates · Heart Health

Your next ten years, from the inside.

Answer a few questions and see your own artery take shape: how likely a heart attack or stroke is in the next ten years, or over a lifetime, and how much of that you can still change. Calculated with the published risk models of European cardiology, entirely in your browser.

Nothing leaves your browser. No account, no cookies.

Your artery, your numbers

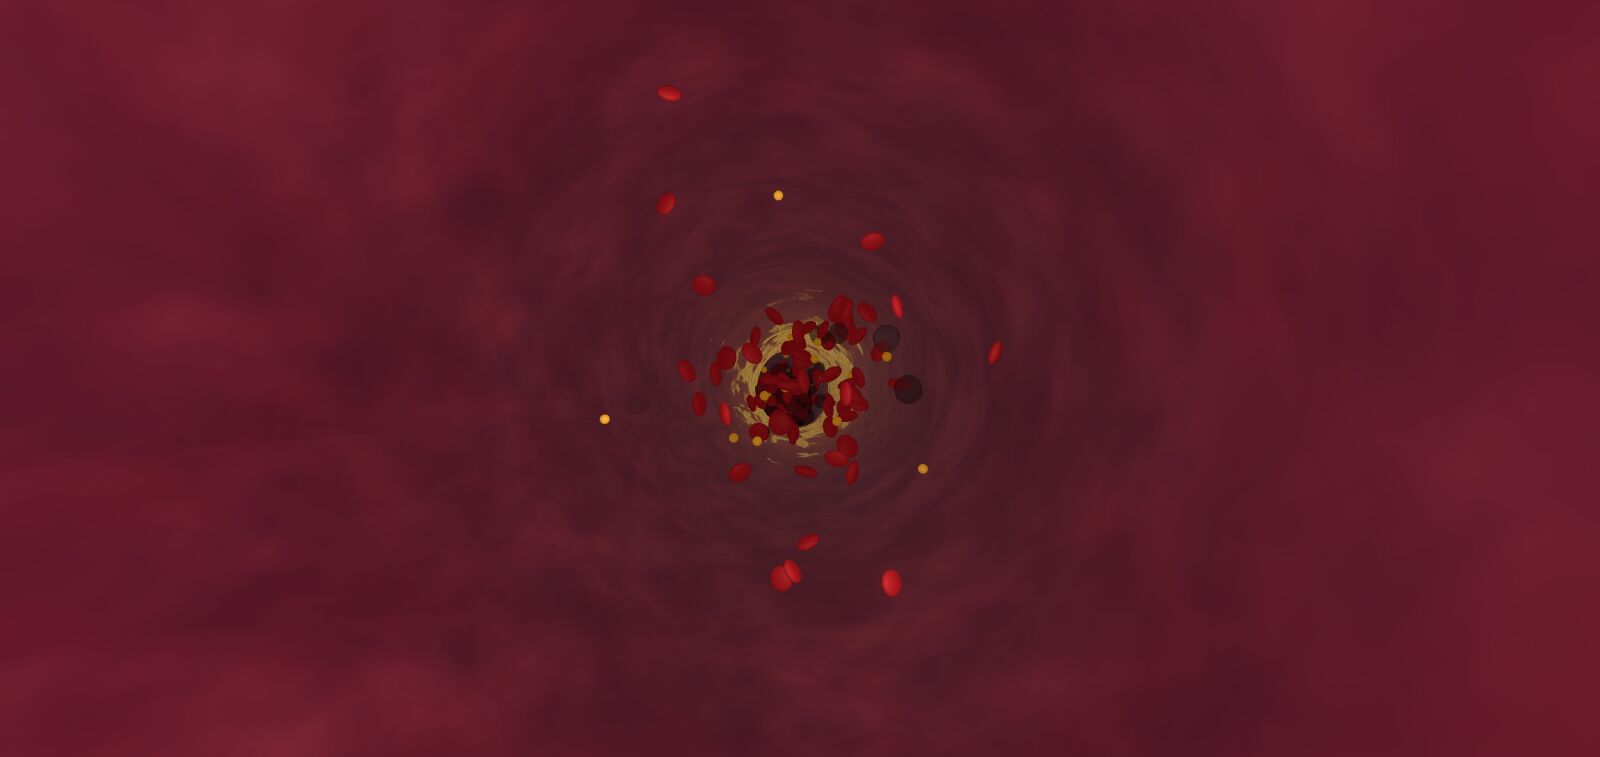
What you see: red cells, yellow LDL particles, plaque on the wall. The narrowing ahead is your risk.

The idea

1

What you can change, and how much

The last step asks what you would do: lower your blood pressure, lower your cholesterol, stop smoking, lose weight. The effect of each comes from the large treatment trials, not from a guess: every 10 mmHg off the systolic pressure takes about a fifth off the risk, every mmol/L off the LDL cholesterol about the same. For stopping smoking we simply calculate the same person as a non-smoker.

Drag the sliders and watch the hundred hearts and the artery answer. Then take the picture to someone who can measure you.

2

Ten years or a lifetime

Doctors mostly talk about the next ten years, because that is what the guidelines and the treatment trials are built on. But a 40-year-old with a bad profile has a small ten-year risk and a large lifetime one; the damage is slow and starts early.

So this calculator has two scopes. Ten years uses the models made for that horizon. Lifetime follows you year by year up to your ninetieth birthday, counting both the chance of a heart attack or stroke and the chance of dying of something else first. In that view we also show the years you can expect to live free of an event, because lifetime risk alone can play tricks: stop smoking and you live longer, and a longer life meets more years of risk.

3

What you see in the artery

The artery on this page is not a picture of your body; it is a picture of your numbers. Every answer changes it. Blood pressure sets the force of the pulse against the wall. Cholesterol sends more yellow LDL particles through the stream and lets plaque build up on the inside. Smoking darkens and inflames the wall. Diabetes sweetens the blood with crystals that irritate it.

Ahead of you, the vessel narrows exactly as much as your risk. When you try an action, the narrowing opens again, live. It is a metaphor, drawn carefully: the numbers behind it are the published models, the artery is how we let you feel them.

4

Risk is a count, not a verdict

Nobody can tell you whether you will have a heart attack. What medicine can do is count. Take a hundred people of your age and sex, with your blood pressure, your cholesterol, your habits, and follow them for ten years. Some of them will have a heart attack or a stroke; most will not.

That count is your risk. We show it as a hundred small hearts, because "7 out of 100" says more than "7 %". And we always show a second count next to it: the same hundred people with ideal values. The gap between the two is what is yours to change.

The science behind the numbers

Six published models, chosen by your answers the way the Dutch cardiovascular risk management guideline does it, plus the treatment effects from the trials. Every source is linked.

Treatment effects

The what-if sliders, all scopes

Lowering systolic blood pressure by 10 mmHg lowers the risk of major cardiovascular events by about 20 % (relative risk 0.80), across starting pressures. Lowering LDL cholesterol by 1 mmol/L lowers it by about 21 to 22 % (we use 0.79). Both come from meta-analyses of the randomised trials, and both are applied multiplicatively to the model's risk.

Source: Ettehad D et al. (Lancet 2016); Cholesterol Treatment Trialists' Collaboration (Lancet 2010). Blood pressure lowering for prevention of cardiovascular disease and death; Efficacy and safety of more intensive lowering of LDL cholesterol. The Lancet 387: 957-967; The Lancet 376: 1670-1681, 2016, 2010.

SMART-REACH

Lifetime, established vascular disease or diabetes

The lifetime companion of SMART, derived in the REACH registry of Western Europe and validated in North America and Utrecht. It estimates the years one can expect to live without a new heart attack or stroke, again with the competing chance of dying of something else. Treatment effects are applied the way the authors do it: as hazard ratios from the trials (a fifth less risk per 10 mmHg systolic, a fifth less per mmol/L LDL).

Source: Kaasenbrood L, Bhatt DL, Dorresteijn JAN et al.. Estimated life expectancy without recurrent cardiovascular events in patients with vascular disease: the SMART-REACH model. Journal of the American Heart Association 7(16): e009217, 2018.

LIFE-CVD

Lifetime, apparently healthy people

A lifetime model built in the Multi-Ethnic Study of Atherosclerosis, with two competing hazards: a heart attack or stroke, and death from another cause. Year by year up to age 90 it follows sex, blood pressure, non-HDL cholesterol, body mass index, smoking (now or before), diabetes and a parent with an early heart attack. It carries its own term for lowering LDL cholesterol; blood pressure, weight and smoking are changed in the profile itself.

Source: Jaspers NEM, Blaha MJ, Matsushita K et al.. Prediction of individualized lifetime benefit from cholesterol lowering, blood pressure lowering, antithrombotic therapy, and smoking cessation in apparently healthy people. European Heart Journal 41(11): 1190-1199, 2020.

SMART

Ten years, established vascular disease

For people who already had a heart attack, stroke, aneurysm or peripheral artery disease. Derived in the SMART cohort of Utrecht and in use in the ESC prevention toolbox. Inputs: age, sex, smoking, systolic blood pressure, diabetes, the locations of vascular disease, years since the first event, HDL and total cholesterol, kidney function and C-reactive protein.

Source: Dorresteijn JAN, Visseren FLJ, Wassink AMJ et al. (SMART Study Group). Development and validation of a prediction rule for recurrent vascular events based on a cohort study of patients with arterial disease: the SMART risk score. Heart 99(12): 866-872, 2013.

ADVANCE

Ten years, type 2 diabetes, no vascular disease

Derived in the ADVANCE trial of 7,168 people with type 2 diabetes. It predicts four-year risk from age at diagnosis, years of diabetes, sex, pulse pressure, treated hypertension, atrial fibrillation, retinopathy, HbA1c, the albumin/creatinine ratio and non-HDL cholesterol; we extend the four-year figure to ten years.

Source: Kengne AP, Patel A, Marre M et al. (ADVANCE Collaborative Group). Contemporary model for cardiovascular risk prediction in people with type 2 diabetes. European Journal of Cardiovascular Prevention and Rehabilitation 18(3): 393-398, 2011.

Older adults (PROSPER)

Ten years, age 70 and over, no diabetes, no vascular disease

Above seventy the classic charts stop. This model was derived in the PROSPER trial of people aged 70 and older and takes competing risks into account: the chance of dying of something else first. It uses sex, age, smoking, systolic blood pressure, LDL and HDL cholesterol, kidney function (eGFR) and statin use.

Source: Stam-Slob MC, Visseren FLJ, Jukema JW et al.. Personalized absolute benefit of statin treatment for primary or secondary prevention of vascular disease in individual elderly patients. Clinical Research in Cardiology 106: 58-68, 2017.

SCORE

Ten years, age 40 to 69, no diabetes, no vascular disease

The risk chart of the European Society of Cardiology, in its low-risk-country version (the Netherlands is one). From sex, age, smoking, systolic blood pressure and total cholesterol it reads the ten-year risk of dying of cardiovascular disease. As the Dutch guideline does, we multiply fatal risk by 3 for men and 4 for women to arrive at the risk of any heart attack or stroke, and by 1.5 for rheumatoid arthritis.

Source: Conroy RM, Pyörälä K, Fitzgerald AP et al. (SCORE project group). Estimation of ten-year risk of fatal cardiovascular disease in Europe: the SCORE project. European Heart Journal 24(11): 987-1003, 2003.
Questions and answers

What is the difference between the SCORE2 calculator and the extended one?

The SCORE2 page runs one algorithm, the model of the 2021 European guideline (SCORE2 from 40 to 69, SCORE2-OP from 70 to 89), on six answers, and shows no treatment effects: you move your own values and the count follows. The extended calculator chooses among six models by your answers, so it also covers diabetes, earlier heart disease and lifetime risk, and it adds a what-if with the treatment effects measured in the trials. For an apparently healthy adult of 40 to 89 the two give similar but not identical numbers: they are different models, built on different cohorts.

Who made this?

Heart Health Calculator is part of Cardio Therapeutic Updates, independent, evidence-based information and education for healthcare professionals. The first version was shown to the public in Zeist in 2021; this edition re-imagines it with a living artery and the same, verified models, and keeps the original app as the third choice.

Can I use mg/dL instead of mmol/L?

Yes, switch the unit on the cholesterol questions; HbA1c accepts both % and mmol/mol. The conversion is done on the page (1 mmol/L = 38.67 mg/dL) and the models always compute in mmol/L.

Where do my answers go?

Nowhere. The models run in your browser; this site has no server-side logic, no account, no analytics script and no cookies. If you share a result, the answers travel inside the link itself, so share it only with people you want to see them.

Why can my lifetime risk go up when I stop smoking?

Because the lifetime models count two things at once: the chance of a heart attack or stroke, and the chance of dying of something else first. A smoker who stops lives longer, and a longer life meets more years in which a heart attack can happen. That is why the lifetime view also shows the years you can expect to live free of an event: that number always improves.

What does "with ideal values" mean?

The second count is the same model for someone of your age and sex who does not smoke, has no diabetes or vascular disease, a systolic pressure of 120 mmHg, total cholesterol of 4.0 mmol/L (LDL 2.5, HDL 1.3) and a body mass index of 23. It is the floor you are compared against, not a target your doctor will necessarily set.

I do not know my cholesterol or blood pressure. Can I still use it?

Yes. Every question has an "I don't know" option. The model then uses the average value of the population it was built in, and the result says so. A blood pressure cuff at the pharmacy and a cholesterol test at your doctor turn the estimate into your own.

Which model is used for me?

That follows from your answers, the way the Dutch cardiovascular risk management guideline does it. Under 70 without diabetes or vascular disease: SCORE. 70 and older: the PROSPER-derived model for older adults. Diabetes: ADVANCE. Established vascular disease: SMART. For the lifetime scope: LIFE-CVD, or SMART-REACH when you have diabetes or vascular disease. The result always names the model used.

Is this calculator accurate for me?

It is as accurate as the published models are: they predict well for groups and are deliberately imprecise for one person. Treat the number as a direction, not a diagnosis. The ranking of what you can change (smoking, blood pressure, cholesterol) is robust; the exact percentage is not.

This calculator is for education and awareness. It estimates the risk of a group of people with values like yours; it does not know you. It is not medical advice and never replaces a conversation with your doctor, who can measure what this page can only ask.

Heart Health Calculator

Educational purposes only

This site is intended for healthcare professionals and provides information for educational purposes. It does not give medical advice about an individual or a patient and offers no medical or diagnostic service. We do not guarantee that the information meets your health or medical needs. If you have any concern about your health, contact a health professional.